




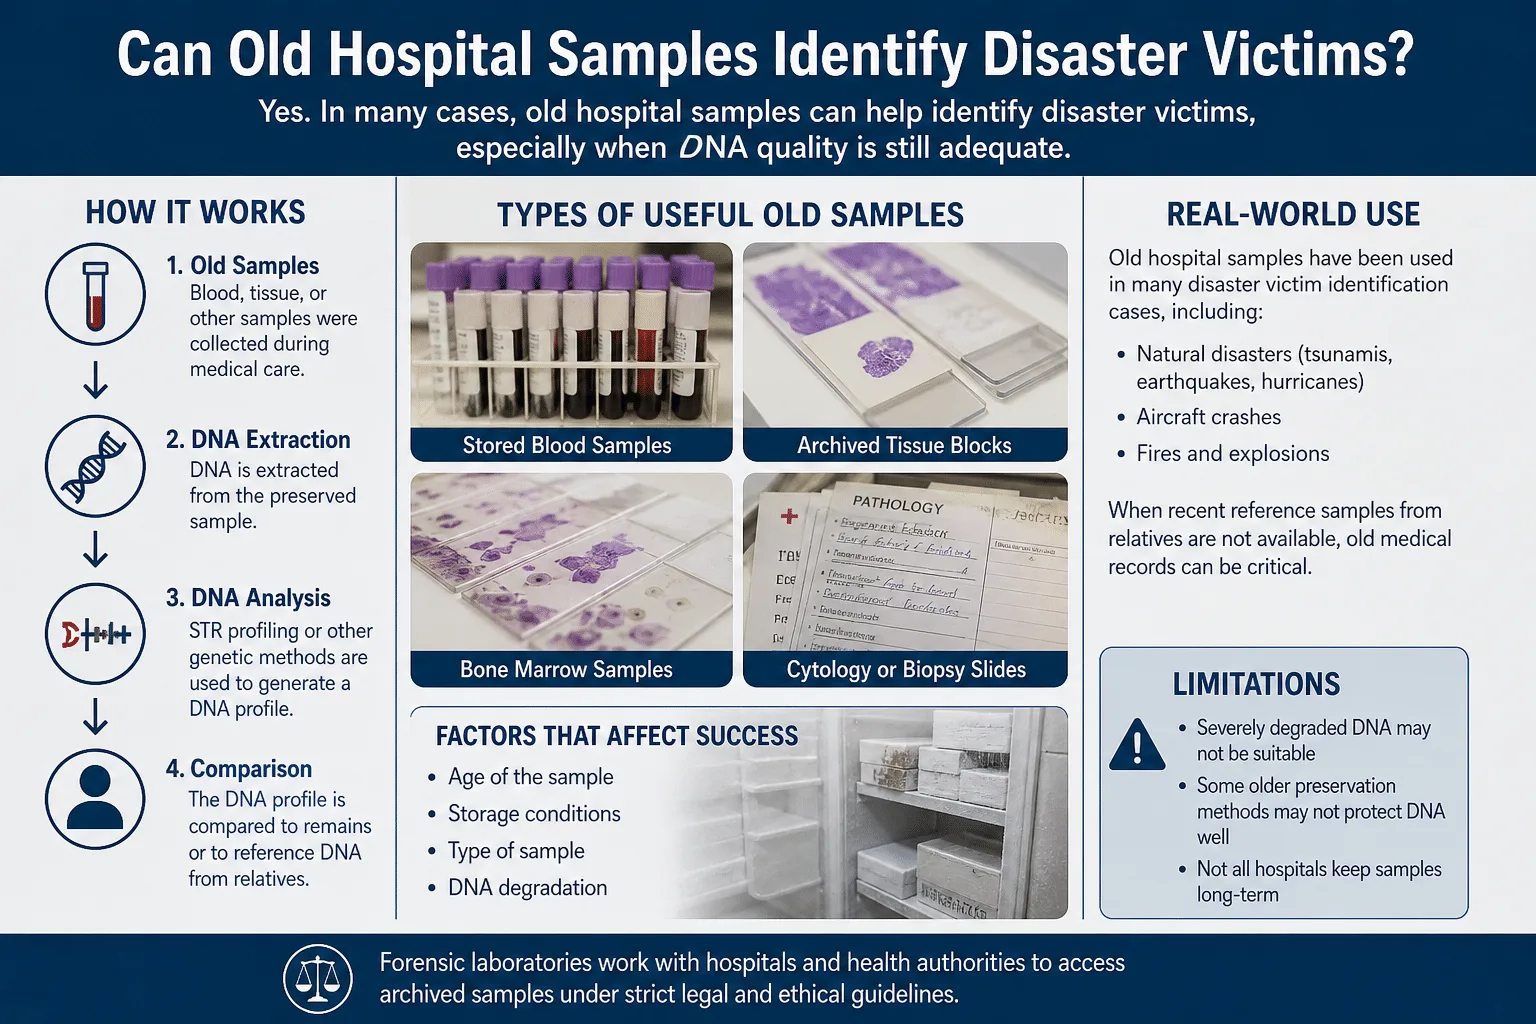
When a disaster destroys personal belongings or leaves few close relatives available for DNADNA, or Deoxyribonucleic Acid, is the genetic material found in cells, composed of a double helix structure. It serves as the genetic blueprint for all Read Full Definition comparison, a hospital archive may hold another reference. A biopsy, diagnostic swab or stored blood sample can provide DNA collected before death. Its value depends on whether the specimen can be traced to the missing person and whether the resulting profile is suitable for comparison with the remains.
- Why disaster victim identification needs antemortem references
- What the 2026 study examined
- Why an archived clinical specimen can be stronger than a personal item
- Which archived specimens are most challenging?
- The laboratory controls that matter
- DNA comparison is not the final identification decision
- Legal, ethical and privacy questions
- What this means for DVI preparedness
- What the study means for identification
Study at a glance
Archived medical specimens as antemortem DNA references for disaster victim identification
Study summary
The study evaluated STR profiling outcomes from 151 archived clinical specimens collected between 2003 and 2023.
Critical appraisal
- Limitations
- The reported range describes mean locus recovery across specimen and processing conditions. It does not measure the proportion of victims identified.
- Implications
- A specimen reliably linked to the missing person can provide a direct antemortem DNA reference.
Why disaster victim identification needs antemortem references
In a DNA-led disaster victim identification (DVI) operation, generating a DNA profile from human remains is only one side of the comparison. Investigators also need reliable antemortem information against which the postmortem profile can be evaluated.
Common DNA reference sources include:
- Direct personal references, such as a toothbrush, razor or stored biological specimen believed to have been used only by the missing person.
- Family-reference samples collected from biological relatives and interpreted using a documented pedigree and kinship statistics.
- Previously generated DNA profiles, where identity, quality and authority for comparison can be established.
Personal items can be shared, mislabeled or contaminated. Family-reference comparisons depend on a reliable pedigree and can be less informative when only distant relatives are available. If several members of the same household are missing, a clinical specimen with a verified accession record may provide a direct reference.
What the 2026 study examined
The new International Journal of Legal Medicine study followed the identification challenges created by the 7 October 2023 attack in Israel. Investigators used Ministry of Health repositories to develop what the authors describe as a “self-direct-reference” antemortem DNA database.
The researchers evaluated 151 archived clinical specimens collected between 2003 and 2023.
- 131 histological specimens, including formalin-fixed paraffin-embedded tissue blocks and cytology slides;
- 8 diagnostic swabs; and
- 12 blood or serum specimens.
The researchers examined whether specimen type, extraction method, incubation protocol and specimen age affected STR profiling. They used the Investigator 24plex system and assessed recovery across 21 autosomal STR loci.
Depending on the specimen type and processing method, the reported mean locus recovery ranged from approximately 67% to 100%.
What the recovery percentages measure
Why an archived clinical specimen can be stronger than a personal item
A properly documented pathology block or diagnostic specimen was collected from a known patient during healthcare. If the specimen identifier, patient identity and repository record remain reliable, the biological material should originate from that patient.
This can offer an evidential advantage over an object collected from a residence. A toothbrush labeled with a person’s name may have been shared, moved or contaminated. A hospital specimen is not automatically immune to error, but it begins with a formal accessioning process and a clinical record that can be independently checked.
The comparison can also be more straightforward. A sufficiently complete direct reference can be compared with the postmortem profile as a same-person proposition. A family sample instead requires a relationship hypothesis, an accurate pedigree, population data and a kinship calculation whose strength depends on the available relatives.
Which archived specimens are most challenging?
Formalin-fixed paraffin-embedded tissue
FFPE tissue is widely retained in pathology archives, but formalin can cross-link DNA to proteins and fragment the molecule. Paraffin removal, tissue digestion and DNA purification therefore require procedures designed for damaged material. Longer storage, fixation conditions, tissue type and block handling can all affect recovery.
Short forensic STR amplicons may still be recovered, but laboratories must anticipate preferential loss of larger targets, allelic dropout and incomplete profiles. Replicate analysis or an alternative marker system may be justified when the comparison is critical and sufficient material remains.
Cytology slides
Cytology preparations can contain limited cellular material. The cells may also have been stained, mounted or exposed to chemicals that affect extraction and amplification. Sampling must preserve as much diagnostic material as possible while avoiding transfer between slides.
Diagnostic swabs and stored blood
These may provide higher-quality DNA, but performance depends on the collection device, storage temperature, preservatives, specimen age and the volume remaining. Serum generally contains less cellular DNA than whole blood and should not be assumed to behave identically.
The laboratory controls that matter
Using an old clinical sample for identification should be treated as a controlled forensic process, not as an informal transfer from a hospital to a DNA laboratory. A defensible workflow should address:
- Identity verification: confirmation that the medical-record identity and specimen accession number refer to the correct patient.
- Documented transfer: tamper-evident packaging, transfer records and continuous chain of custody.
- ContaminationContamination - The unwanted transfer of material from another source to a piece of physical evidence. The inadvertent touching of a weapon, thereby adding fingerprints Read Full Definition assessment: reagent blanks, appropriate positive and negative controls, staff elimination procedures and review of previous handling.
- Sample conservation: justification of how much material is consumed and whether clinically important material must remain available.
- Method suitability: validated extraction and profiling procedures for the relevant specimen type and degree of degradation.
- Replicate or confirmatory analysis: especially for partial profiles, unexpected mixtures or low-template findings.
- Independent review: technical and administrative review before the profile enters the comparison and reconciliation process.
DNA comparison is not the final identification decision
International DVI practice separates the collection and analysis of antemortem information, the examination of human remains and the final reconciliation process. DNA is one primary identification method, alongside methods such as fingerprintsFingerprint, impression made by the papillary ridges on the ends of the fingers and thumbs. Fingerprints afford an infallible means of personal identification, because the Read Full Definition and dental comparison, but the result must remain connected to the correctly numbered remains.
This distinction is crucial in fragmented or commingled cases. A scientifically correct DNA profile can still contribute to a wrong identification if a bone, tooth, tissue sample or temporary mortuary number was assigned incorrectly. Duplicate sampling can also make one person appear to represent several unidentified sets of remains.
Accordingly, a strong DNA association should be reconciled with:
- recovery location and remains numbering;
- anthropological assessment and commingling review;
- dental, fingerprint and medical evidence where available;
- the missing-person list and verified demographic information;
- duplicate-profile searches; and
- documented authority for the final identification decision.
Legal, ethical and privacy questions
Material retained for diagnosis was not necessarily collected with disaster identification in mind. Its later forensic use therefore raises questions beyond analytical performance.
Authorities need a clear legal basis for access and transfer. Health-information confidentiality, consent rules, retention law and judicial or emergency powers differ between jurisdictions. Governance should also define who may search the resulting profiles, how long data are retained and whether the information may be repurposed for criminal investigation, research or database searching.
The principle of data minimization is particularly important. A DVI program usually needs identity-relevant genetic information—not unrestricted access to medical records or genome-wide health information. STR profiling and record handling should be limited to the legitimate identification purpose, with access logs and defined deletion or return procedures.
What this means for DVI preparedness
The study suggests that medical repositories should be considered during preparedness planning rather than only after conventional references fail. That does not mean every hospital specimen should be preemptively profiled. It means DVI plans should establish, before a disaster:
- which repositories retain potentially useful specimens;
- who has authority to request and release them;
- how identity and accession records will be verified;
- which laboratories can process FFPE and other archived material;
- how limited clinical material will be conserved;
- how profiles will be exchanged securely; and
- how results will enter the formal reconciliation process.
Cross-border disasters make this planning even more important. The remains, relatives, medical records and pathology specimens may be held in different jurisdictions, each with its own privacy, evidentiary and data-transfer requirements.
What the study means for identification
The study shows that archived specimens can yield useful STR data years after collection. For a DVI team, the practical decision is whether each specimen can be traced to the right person, whether its profile supports the proposed comparison, and whether the result can be reconciled with the records for the remains. Access to the specimen and handling of the resulting profile require separate governance decisions.
Frequently asked questions
Can an archived hospital specimen provide a direct DNA reference?
Yes, if records reliably link it to the missing person and the laboratory obtains a profile suitable for comparison.
What does 67–100% mean locus recovery mean?
It is the average proportion of informative STR loci recovered under different specimen and processing conditions. It does not report the percentage of specimens yielding complete profiles or the percentage of victims identified.
SourceDoes a DNA comparison complete a DVI identification?
The comparison is evaluated during reconciliation alongside the specimen and remains records and other available identification evidence.
SourceReferences & Sources
Show referencesHide references
- Ido A, Avrahami K, Feinberg T, Itzhaki-Alfia A, Herman Y. Archived medical specimens as antemortem DNA references for disaster victim identification, optimization study following the October 7 massacre. International Journal of Legal Medicine. Published 30 September 2026. Source DOI: 10.1007/s00414-026-04028-0
- INTERPOL. Disaster Victim Identification (DVI). Source
This article discusses the scientific and operational implications of newly published research. Local law, ethics requirements and accredited laboratory procedures govern the use of clinical specimens in actual identification operations.





